T-cell Engagers (TCEs): Data-Driven Development Insights

May 27, 2025

TCEs: Expanding the scope of precision immunotherapies  

T-cell engagers (TCEs) are typically bispecific antibodies that bind to both a disease-associated antigen and the CD3 protein on T cells, physically linking T cells to pathogenic cells and activating cytotoxic responses irrespectively of the patient’s HLA status.

Unlike personalized cell therapies, TCEs are off-the-shelf biologics that can be manufactured at scale, rapidly deployed, and administered in standard clinical settings without lymphodepletion. Combined with their ability to engage native T cells without genetic modification, TCEs also carry a favorable safety profile, with lower rates and severity of cytokine release syndrome (CRS), and lower risk of long-term T-cell malignancy as compared to cell-based therapies.

Since the first approval of TCE therapy in 2014, the number of TCEs entering the market has steeply increased over the past 3 years (Figure 1), and their use is expanding into new clinical areas, including autoimmune diseases, solid tumors, and infectious diseases, with both novel and repurposed targets.
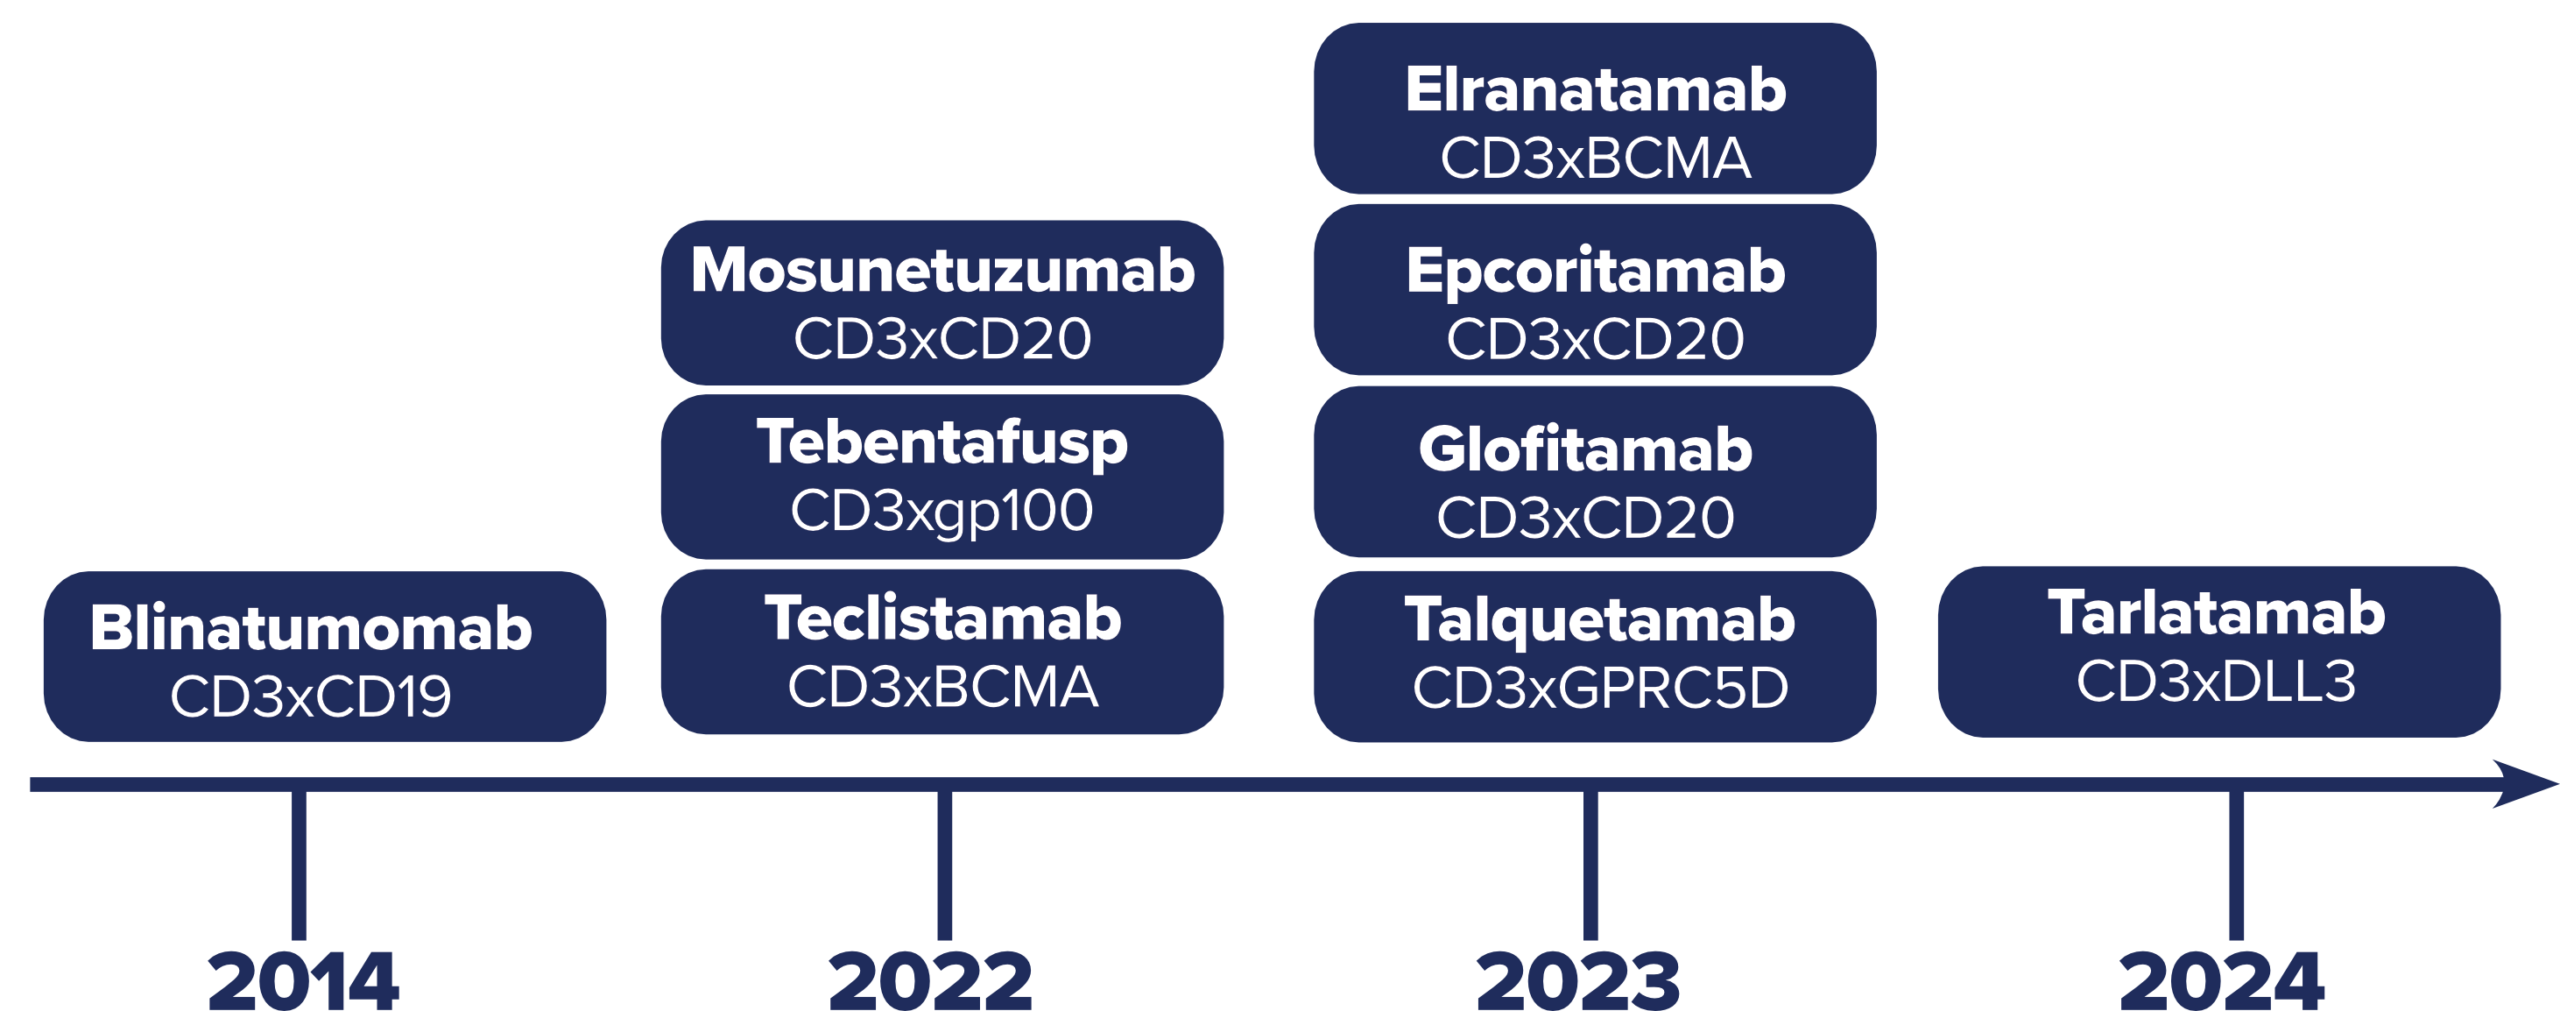
 

Figure 1: Timeline of TCE FDA approvals

As TCEs expand into new indications and patient populations, they offer a valuable opportunity for developers. But to successfully bring a TCE through clinical development and into regulatory approval, developers must generate a detailed understanding of the complex dynamics that shape TCE patient responses.

Generating the data you need to advance TCE development

Successful TCE development requires a clear understanding of specific aspects of therapeutic behavior, through detailed, targeted analysis. Selecting the appropriate parameters to measure is essential to generate meaningful insights that can guide clinical decision-making and development strategy.

1- Confirming target expression

Confirmation of target expression is essential to determine the potential of drug engagement—a prerequisite for efficacy. Developing precise target expression data is also critical for patient selection and stratification, companion diagnostic development, and evaluating off-target effects.

To generate this data, developers may assess expression in solid tumors using immunohistochemistry or immunofluorescence, or in peripheral or biopsy samples using flow cytometry. These approaches provide reliable data on whether the intended antigen is sufficiently present.

2- Assessing long-term efficacy

The success of TCEs depends on creating sustained immune activity. Demonstrating the long-term efficacy and curative potential of TCEs requires extended follow-ups—particularly for newer indications such as solid tumors or autoimmune diseases.

To get these insights, developers must monitor pathogenic cell populations over time, using flow cytometry for liquid samples or immunohistochemistry or immunofluorescence for tissue, and correlate these findings with longitudinal clinical data.

3- Understanding the mechanisms of primary resistance

Not all patients respond to TCE therapy, and understanding pre-existing T-cell landscapes is critical to predicting which patients will benefit most from treatment. Developers must establish baseline composition of the T-cell compartment early in development to identify immune signatures that predict response or resistance.

To do so, developers can apply high-dimensional spectral flow cytometry phenotyping panels to characterize surface markers and immune subsets in detail. Additionally, single-cell resolution assays that combine transcriptomic, proteomic, and T cell repertoire data can provide a more integrated view of T-cell status to help predict clinical response.

4- Tracking acquired resistance

Even in patients who respond to TCE treatment initially, T cells may lose function over time due to sustained activation, imposing major constraints on the drug’s therapeutic efficacy. Detecting this shift in response throughout treatment requires the assessment of T-cell activation and exhaustion markers.

This can be achieved using standardized flow cytometry panels with widely used markers for exhaustion (e.g., PD-1, TIM-3, LAG3, CD39), and activation (e.g., CD69, CD38, HLA-DR). In parallel, enumeration panels can be used to track pathogenic cell counts and help correlate changes in T-cell state with therapeutic efficacy—providing the data needed to inform treatment adjustments.

5- Assessing safety risks

While TCEs generally offer a favorable safety profile compared to cell-based therapies, there are still risks of adverse effects, like CRS and immune effector cell-associated neurotoxicity syndrome (ICANS), that must be assessed.

To support this, developers can deploy cytokine profiling during early clinical phases to capture broad inflammatory responses. Several immunoassay platforms, including Olink®, MSD®, and ELLA™, can be used to enable sensitive, multiplexed measurement of cytokine levels and understand the risk of adverse effects.

Building a strong foundation for successful TCE development

TCEs offer clear advantages as a scalable and versatile immunotherapy platform, but their successful development depends on a deep understanding of how these therapies perform. Monitoring key parameters such as target expression, immune activation, and resistance over time is essential to generate the evidence required to advance confidently through development.

As TCEs expand into new indications, developers who can integrate these insights early will be best positioned to navigate complexity, reduce uncertainty, and make informed decisions that move their therapies forward.

CellCarta can support your TCE program with the capabilities and expertise needed to drive confident development. Get in touch with our experts to find out more.

About the author:

author photo

Céline Vandamme is a Scientific Business Director at CellCarta, specializing in the flow cytometry platform. With a PhD in immunology, and a broad expertise gained through her work at various academic and pharmaceutical institutions, Céline has profuse experience in designing flow cytometry assays to support immune monitoring activities in clinical trials.
T-cell Engagers (TCEs): Data-Driven Development Insights

May 27, 2025

TCEs: Expanding the scope of precision immunotherapies  

T-cell engagers (TCEs) are typically bispecific antibodies that bind to both a disease-associated antigen and the CD3 protein on T cells, physically linking T cells to pathogenic cells and activating cytotoxic responses irrespectively of the patient’s HLA status.

Unlike personalized cell therapies, TCEs are off-the-shelf biologics that can be manufactured at scale, rapidly deployed, and administered in standard clinical settings without lymphodepletion. Combined with their ability to engage native T cells without genetic modification, TCEs also carry a favorable safety profile, with lower rates and severity of cytokine release syndrome (CRS), and lower risk of long-term T-cell malignancy as compared to cell-based therapies.

Since the first approval of TCE therapy in 2014, the number of TCEs entering the market has steeply increased over the past 3 years (Figure 1), and their use is expanding into new clinical areas, including autoimmune diseases, solid tumors, and infectious diseases, with both novel and repurposed targets.


Figure 1: Timeline of TCE FDA approvals

As TCEs expand into new indications and patient populations, they offer a valuable opportunity for developers. But to successfully bring a TCE through clinical development and into regulatory approval, developers must generate a detailed understanding of the complex dynamics that shape TCE patient responses.

Generating the data you need to advance TCE development

Successful TCE development requires a clear understanding of specific aspects of therapeutic behavior, through detailed, targeted analysis. Selecting the appropriate parameters to measure is essential to generate meaningful insights that can guide clinical decision-making and development strategy.

1- Confirming target expression

Confirmation of target expression is essential to determine the potential of drug engagement—a prerequisite for efficacy. Developing precise target expression data is also critical for patient selection and stratification, companion diagnostic development, and evaluating off-target effects.

To generate this data, developers may assess expression in solid tumors using immunohistochemistry or immunofluorescence, or in peripheral or biopsy samples using flow cytometry. These approaches provide reliable data on whether the intended antigen is sufficiently present.

2- Assessing long-term efficacy

The success of TCEs depends on creating sustained immune activity. Demonstrating the long-term efficacy and curative potential of TCEs requires extended follow-ups—particularly for newer indications such as solid tumors or autoimmune diseases.

To get these insights, developers must monitor pathogenic cell populations over time, using flow cytometry for liquid samples or immunohistochemistry or immunofluorescence for tissue, and correlate these findings with longitudinal clinical data.

3- Understanding the mechanisms of primary resistance

Not all patients respond to TCE therapy, and understanding pre-existing T-cell landscapes is critical to predicting which patients will benefit most from treatment. Developers must establish baseline composition of the T-cell compartment early in development to identify immune signatures that predict response or resistance.

To do so, developers can apply high-dimensional spectral flow cytometry phenotyping panels to characterize surface markers and immune subsets in detail. Additionally, single-cell resolution assays that combine transcriptomic, proteomic, and T cell repertoire data can provide a more integrated view of T-cell status to help predict clinical response.

4- Tracking acquired resistance

Even in patients who respond to TCE treatment initially, T cells may lose function over time due to sustained activation, imposing major constraints on the drug’s therapeutic efficacy. Detecting this shift in response throughout treatment requires the assessment of T-cell activation and exhaustion markers.

This can be achieved using standardized flow cytometry panels with widely used markers for exhaustion (e.g., PD-1, TIM-3, LAG3, CD39), and activation (e.g., CD69, CD38, HLA-DR). In parallel, enumeration panels can be used to track pathogenic cell counts and help correlate changes in T-cell state with therapeutic efficacy—providing the data needed to inform treatment adjustments.

5- Assessing safety risks

While TCEs generally offer a favorable safety profile compared to cell-based therapies, there are still risks of adverse effects, like CRS and immune effector cell-associated neurotoxicity syndrome (ICANS), that must be assessed.

To support this, developers can deploy cytokine profiling during early clinical phases to capture broad inflammatory responses. Several immunoassay platforms, including Olink®, MSD®, and ELLA™, can be used to enable sensitive, multiplexed measurement of cytokine levels and understand the risk of adverse effects.

Building a strong foundation for successful TCE development

TCEs offer clear advantages as a scalable and versatile immunotherapy platform, but their successful development depends on a deep understanding of how these therapies perform. Monitoring key parameters such as target expression, immune activation, and resistance over time is essential to generate the evidence required to advance confidently through development.

As TCEs expand into new indications, developers who can integrate these insights early will be best positioned to navigate complexity, reduce uncertainty, and make informed decisions that move their therapies forward.

CellCarta can support your TCE program with the capabilities and expertise needed to drive confident development. Get in touch with our experts to find out more.

About the author:

author photo

Céline Vandamme is a Scientific Business Director at CellCarta, specializing in the flow cytometry platform. With a PhD in immunology, and a broad expertise gained through her work at various academic and pharmaceutical institutions, Céline has profuse experience in designing flow cytometry assays to support immune monitoring activities in clinical trials.

Solutions for T cell engager (TCE) programs

May 16, 2025

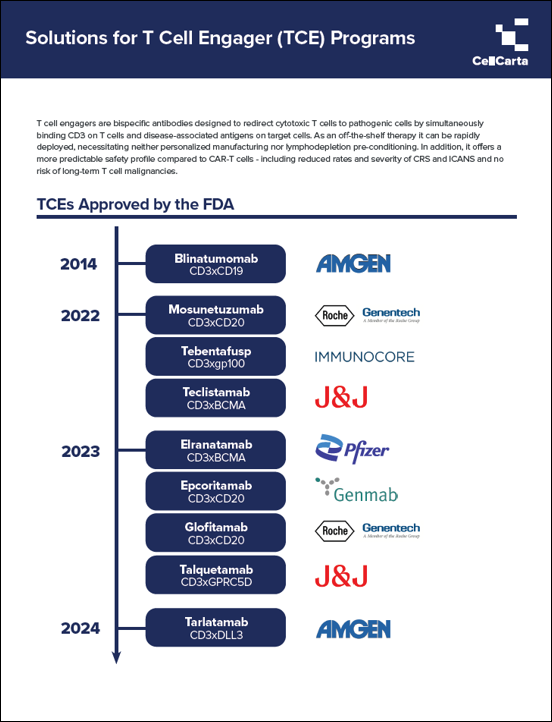
T cell engagers (TCEs) are bispecific antibodies designed to redirect cytotoxic T cells to pathogenic cells by simultaneously binding CD3 on T cells and disease-associated antigens on target cells.

Key limitations of T cell engager therapies include an incomplete understanding of primary resistance to treatment, which is influenced by the baseline composition of the T cell compartment and acquired resistance that is driven by T cell exhaustion.

In addition to supporting the assessment of safety and efficacy, CellCarta can also help you unravel the mechanisms at play behind primary and acquired resistance to TCE therapies. 

Link to brochure

Solutions for T cell engager (TCE) programs

May 16, 2025

T cell engagers (TCEs) are bispecific antibodies designed to redirect cytotoxic T cells to pathogenic cells by simultaneously binding CD3 on T cells and disease-associated antigens on target cells.

Key limitations of T cell engager therapies include an incomplete understanding of primary resistance to treatment, which is influenced by the baseline composition of the T cell compartment and acquired resistance that is driven by T cell exhaustion.

In addition to supporting the assessment of safety and efficacy, CellCarta can also help you unravel the mechanisms at play behind primary and acquired resistance to TCE therapies. 

Link to brochure

Comparable detection of large tumor-derived vesicles (oncosomes) by known CTC platforms: potential new analyte for biomarker monitoring?

April 27, 2025

Comparable detection of large tumor-derived vesicles (oncosomes) by known CTC platforms: potential new analyte for biomarker monitoring?

Comparable detection of large tumor-derived vesicles (oncosomes) by known CTC platforms: potential new analyte for biomarker monitoring?

April 27, 2025

Comparable detection of large tumor-derived vesicles (oncosomes) by known CTC platforms: potential new analyte for biomarker monitoring?

Biomarkers & AI in Future ADCs: Dr. Powles’ Insights

March 17, 2025

Antibody-drug conjugates (ADCs) are changing cancer treatment for the better, combining precision-targeting of cancer cells with the potency of chemotherapy.  

Perhaps one of the most exciting recent advances in ADCs was seen in a trial led by renowned oncologist Dr Thomas Powles. The combination treatment of enfortumab vedotin (EV), a nectin-4 ADC, and pembrolizumab (pembro), a PD-1 inhibitor, more than doubled the median survival of metastatic bladder cancer patients, from one year with standard chemotherapy, to two and a half years.   

Thanks to these transformative results, EV-pembro has superseded traditional platinum-based chemotherapy as the first-line treatment, and Dr Powles believes a cure for bladder cancer is now possible—something that would have seemed unimaginable just a few years ago.  

In our latest Let’s Talk webcast, we had the privilege of talking to Dr Powles about the future possibilities of ADCs. While in our previous blog we discussed his thoughts on the future of ADCs in cancer treatment, here we summarize his insights on the pivotal role that biomarkers and AI could play in their development.  

The importance of biomarkers in future ADC development

As with many other new precision medicine therapeutic strategies, a key hurdle in ADC development is understanding why some patients benefit more than others. While EV-pembro is broadly effective in treating bladder cancer, since nectin-4 is expressed in 90% of the cancer cells, there are still some patients that show limited benefit, and understanding why has proven challenging. Identifying biomarkers to stratify subtle differences in patient profiles may be crucial to achieving better outcomes.  

“If we’re going to cure bladder cancer, we may not do so with EV-pembro alone,” said Dr Powles. “While it could serve as a baseline treatment for many, we must understand why some patients don’t respond as well, and how we can improve their response, if we are going to achieve a cure.”  

“That’s where the second generation of biomarkers come in“ he continues. “Using transcriptomics and multiplex analysis, we could see what’s expressed in non-responders and find out whether we should be using other agents or more complex immune therapy for those patients.” 

Dr Powles believes that biomarkers will be key to ADC breakthroughs beyond bladder cancer, too. “Deep down, I think the transformative result we’ve seen with EV-pembro in bladder cancer is not a black swan event,” he said. “I think it’s possible in subsets of other cancers.” 

While other ADCs have shown promise, such as those directed at TROP2 and HER2, patient selection criteria remain imprecise, confounding their real effectiveness.  

For TROP2 ADCs, such as sacituzumab govitecan, despite rapid progress, a more refined biomarker strategy is still needed to identify the patients who will benefit the most from this treatment. Similarly, with the HER2-low breast cancer ADC trastuzumab deruxtecan, there is debate around how HER2 expression levels correlate with response rates. HER2 scoring methods can produce inconsistent results, therefore more precise biomarker assessment could substantially improve treatment outcomes.

The role of AI in future ADC development

To help in advancing ADC development, researchers are looking to leverage AI technologies to improve biomarker assessment. Traditional pathology methods rely on human interpretation, which can lead to inconsistencies in how biomarkers are assessed across different labs and clinical settings.

“Diagnostic pathology using AI can bring a standardization that currently isn’t possible with traditional methods,” said Powles. “So far, we haven’t been overly successful with biomarker development. To move forwards, we need AI technology to reduce variability and improve accuracy in patient selection.”

Currently, researchers are investigating the use of AI in identifying responders and non-responders for TROP2 ADCs. When it comes to their use in lung cancer treatment, Dr Powles states: “If you can find the 30% of patients that have a strong response, that could potentially be transformative. If we’re not currently seeing any improvement over traditional chemotherapy with TROP2 ADCs, then we need to find a smarter way of assessing biomarkers, and that could be through AI.”

Looking ahead

The future of ADCs holds great promise, with refined biomarker assessment and AI potentially playing a pivotal role in the development of more personalized therapies in finely-stratified patient cohorts.  

In the full webcast, Dr Powles shares his thoughts on the current and future treatment landscape of ADCs, including where he believes there is most potential for another breakthrough ADC treatment, and the technologies and strategies that could drive their development.  

Don’t miss out on hearing the firsthand insights of a true ADC expert—watch the webcast on demand today: Webcast – Thomas Powles – Gated | CellCarta.

About the author:

author photo

Céline Vandamme is a Scientific Business Director at CellCarta, specializing in the flow cytometry platform. With a PhD in immunology, and a broad expertise gained through her work at various academic and pharmaceutical institutions, Céline has profuse experience in designing flow cytometry assays to support immune monitoring activities in clinical trials.

Biomarkers & AI in Future ADCs: Dr. Powles’ Insights

March 17, 2025

Antibody-drug conjugates (ADCs) are changing cancer treatment for the better, combining precision-targeting of cancer cells with the potency of chemotherapy.  

Perhaps one of the most exciting recent advances in ADCs was seen in a trial led by renowned oncologist Dr Thomas Powles. The combination treatment of enfortumab vedotin (EV), a nectin-4 ADC, and pembrolizumab (pembro), a PD-1 inhibitor, more than doubled the median survival of metastatic bladder cancer patients, from one year with standard chemotherapy, to two and a half years.   

Thanks to these transformative results, EV-pembro has superseded traditional platinum-based chemotherapy as the first-line treatment, and Dr Powles believes a cure for bladder cancer is now possible—something that would have seemed unimaginable just a few years ago.  

In our latest Let’s Talk webcast, we had the privilege of talking to Dr Powles about the future possibilities of ADCs. While in our previous blog we discussed his thoughts on the future of ADCs in cancer treatment, here we summarize his insights on the pivotal role that biomarkers and AI could play in their development.  

The importance of biomarkers in future ADC development

As with many other new precision medicine therapeutic strategies, a key hurdle in ADC development is understanding why some patients benefit more than others. While EV-pembro is broadly effective in treating bladder cancer, since nectin-4 is expressed in 90% of the cancer cells, there are still some patients that show limited benefit, and understanding why has proven challenging. Identifying biomarkers to stratify subtle differences in patient profiles may be crucial to achieving better outcomes.  

“If we’re going to cure bladder cancer, we may not do so with EV-pembro alone,” said Dr Powles. “While it could serve as a baseline treatment for many, we must understand why some patients don’t respond as well, and how we can improve their response, if we are going to achieve a cure.”  

“That’s where the second generation of biomarkers come in“ he continues. “Using transcriptomics and multiplex analysis, we could see what’s expressed in non-responders and find out whether we should be using other agents or more complex immune therapy for those patients.” 

Dr Powles believes that biomarkers will be key to ADC breakthroughs beyond bladder cancer, too. “Deep down, I think the transformative result we’ve seen with EV-pembro in bladder cancer is not a black swan event,” he said. “I think it’s possible in subsets of other cancers.” 

While other ADCs have shown promise, such as those directed at TROP2 and HER2, patient selection criteria remain imprecise, confounding their real effectiveness.  

For TROP2 ADCs, such as sacituzumab govitecan, despite rapid progress, a more refined biomarker strategy is still needed to identify the patients who will benefit the most from this treatment. Similarly, with the HER2-low breast cancer ADC trastuzumab deruxtecan, there is debate around how HER2 expression levels correlate with response rates. HER2 scoring methods can produce inconsistent results, therefore more precise biomarker assessment could substantially improve treatment outcomes.

The role of AI in future ADC development

To help in advancing ADC development, researchers are looking to leverage AI technologies to improve biomarker assessment. Traditional pathology methods rely on human interpretation, which can lead to inconsistencies in how biomarkers are assessed across different labs and clinical settings.

“Diagnostic pathology using AI can bring a standardization that currently isn’t possible with traditional methods,” said Powles. “So far, we haven’t been overly successful with biomarker development. To move forwards, we need AI technology to reduce variability and improve accuracy in patient selection.”

Currently, researchers are investigating the use of AI in identifying responders and non-responders for TROP2 ADCs. When it comes to their use in lung cancer treatment, Dr Powles states: “If you can find the 30% of patients that have a strong response, that could potentially be transformative. If we’re not currently seeing any improvement over traditional chemotherapy with TROP2 ADCs, then we need to find a smarter way of assessing biomarkers, and that could be through AI.”

Looking ahead

The future of ADCs holds great promise, with refined biomarker assessment and AI potentially playing a pivotal role in the development of more personalized therapies in finely-stratified patient cohorts.  

In the full webcast, Dr Powles shares his thoughts on the current and future treatment landscape of ADCs, including where he believes there is most potential for another breakthrough ADC treatment, and the technologies and strategies that could drive their development.  

Don’t miss out on hearing the firsthand insights of a true ADC expert—watch the webcast on demand today: Webcast – Thomas Powles – Gated | CellCarta.

About the author:

author photo

Céline Vandamme is a Scientific Business Director at CellCarta, specializing in the flow cytometry platform. With a PhD in immunology, and a broad expertise gained through her work at various academic and pharmaceutical institutions, Céline has profuse experience in designing flow cytometry assays to support immune monitoring activities in clinical trials.
Development of a Pathologist Scoring Method to Determine Inflamed, Excluded or Desert Immune Phenotype in Carcinoma

March 5, 2025

Development of a Pathologist Scoring Method to Determine Inflamed, Excluded or Desert Immune Phenotype in Carcinoma

scoring metiodd to determine inflamed, excluded or desert Immune Phenotype in Carcinoma

Development of a Pathologist Scoring Method to Determine Inflamed, Excluded or Desert Immune Phenotype in Carcinoma

March 5, 2025

Development of a Pathologist Scoring Method to Determine Inflamed, Excluded or Desert Immune Phenotype in Carcinoma

scoring metiodd to determine inflamed, excluded or desert Immune Phenotype in Carcinoma